Sep 21, 2026
Benjamin Brown
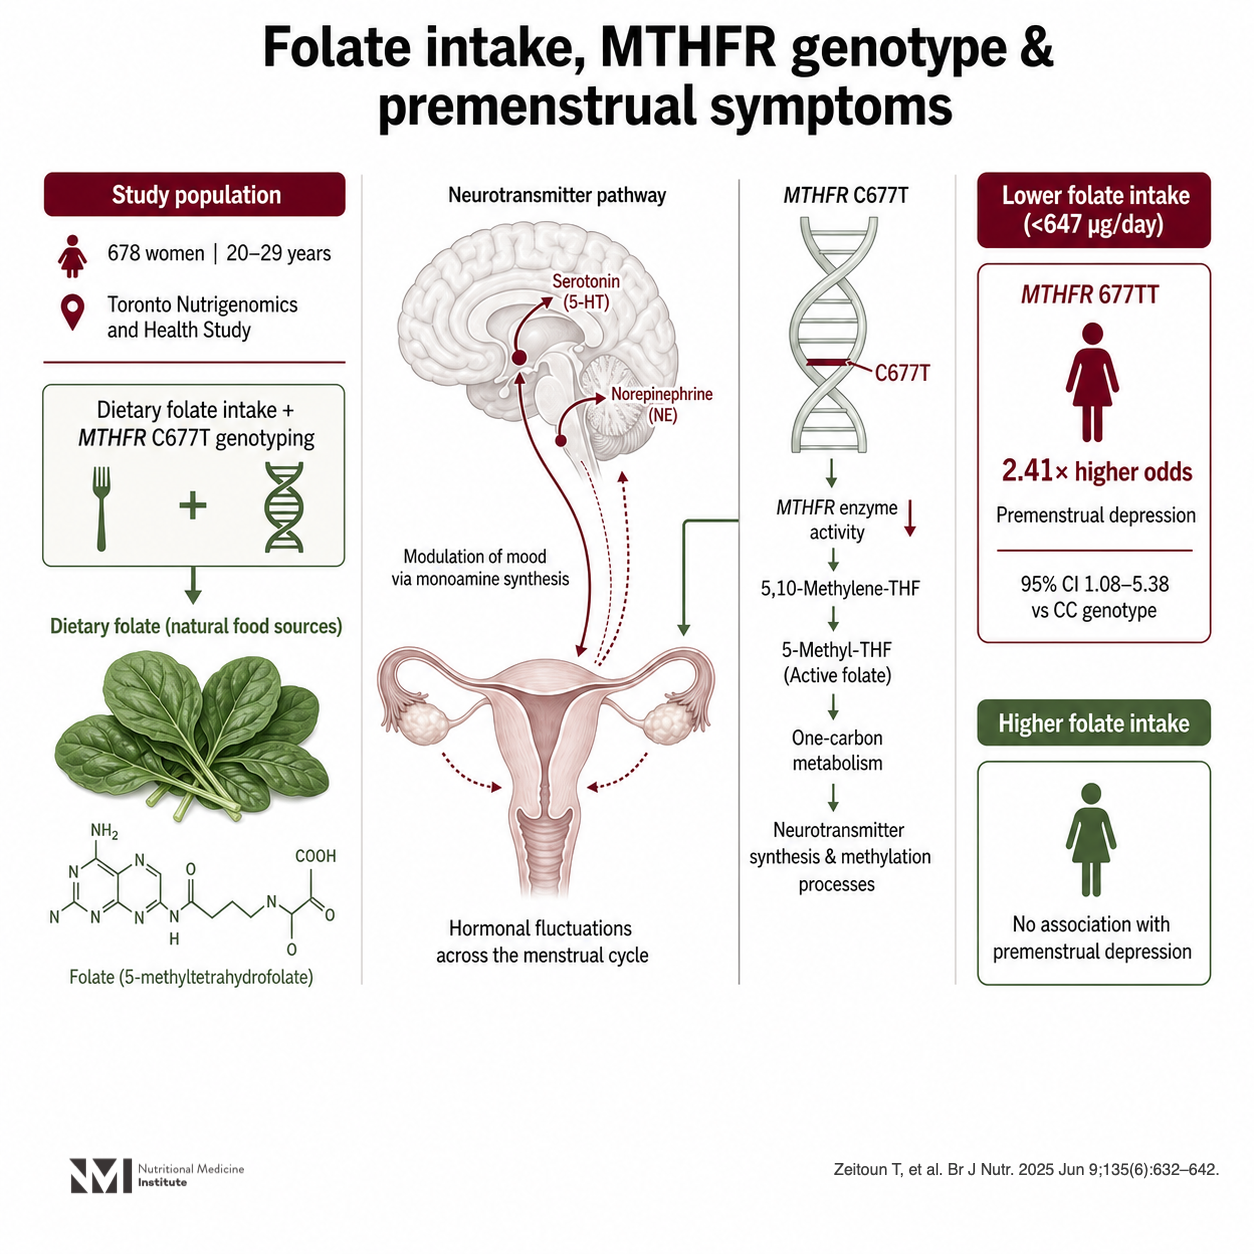
New nutrigenomic evidence links folate metabolism with premenstrual depression. Zeitoun and colleagues1 report that the common MTHFR C677T variant was associated with higher odds of premenstrual depressive symptoms—but only among women with lower habitual folate intake. The finding adds biological insight to a symptom domain too often dismissed as inevitable.
Premenstrual symptoms can impair work, relationships, and quality of life. For a smaller proportion of women, cyclical mood symptoms meet criteria for premenstrual dysphoric disorder (PMDD), requiring careful assessment and evidence-based management. Nutrition is an appealing modifiable factor, yet broad claims about individual nutrients often outpace the evidence. This study takes a more nuanced approach: rather than asking whether folate is uniformly protective, it investigates whether genotype alters the association.
The researchers analysed 678 women aged 20–29 years from the Toronto Nutrigenomics and Health Study. Participants reported 15 premenstrual symptoms, completed a validated food-frequency questionnaire, and underwent MTHFR C677T (rs1801133) genotyping. Total folate intake was divided at the cohort median of 647 µg/day. Among women below that threshold, the odds of reporting premenstrual depression rose across T-allele carriage: adjusted odds ratios were 1.66 for CT and 2.41 for TT, compared with CC. The confidence interval for CT crossed unity, whereas the TT estimate was statistically significant. No such association was observed in women with higher folate intake.
Study highlights:
- Low folate intake plus the MTHFR 677T allele correlated with premenstrual depression.
- TT homozygosity had the strongest association, with an adjusted odds ratio of 2.41.
- Overall folate intake was not independently associated with premenstrual symptom burden.
- The observational design cannot establish benefit from folate supplementation or genotype-directed care.
The biological hypothesis is plausible. MTHFR contributes to producing 5-methyltetrahydrofolate, a key participant in one-carbon metabolism and methylation pathways supporting monoamine synthesis. However, plausible biology does not establish causation. Folate intake and symptoms were self-reported, biomarkers of folate status were unavailable, and the young university-based sample excluded hormonal-contraceptive users and people taking antidepressants or anxiolytics.
Clinically, the results should prompt better nutritional assessment, supporting intake of folate-rich foods and nutritional adequacy where intake may be low and folate supplementation where appropriate. MTHFR testing alone cannot guide treatment but may complement care.
This study identifies a potentially meaningful association between folate metabolism and premenstrual depression. It supports further precision-nutrition research and the need for intervention trials incorporating folate biomarkers, genotype, and validated PMS/PMDD outcomes.